
Before FiLaC
The fistula route must be understood and any abscess controlled. Some patients need MRI, ultrasound, a seton or another procedure first.
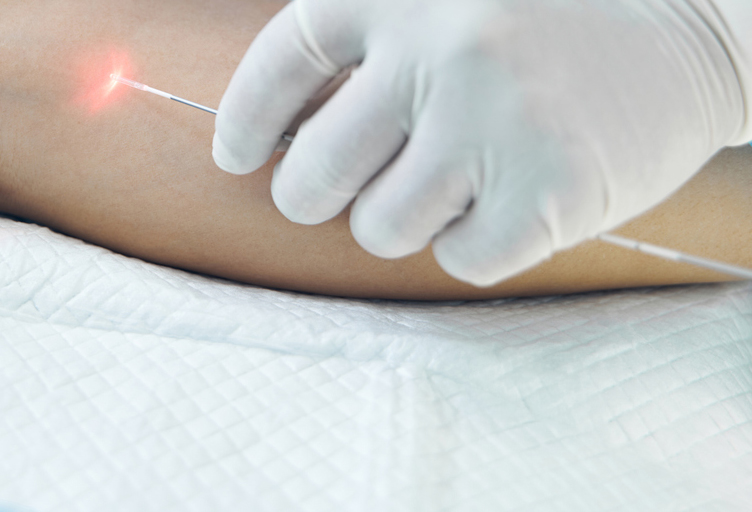
FiLaC uses a flexible laser fibre inside an anal fistula. Energy is delivered around the tract as the fibre is pulled back. The aim is to close the tunnel without cutting through the sphincter muscles that help control the bowel.
Sometimes, but a shallow simple fistula may heal more reliably after fistulotomy (a simple cut) with a low risk to muscle. The choice must be individual.
There are usually small openings rather than a long laid-open wound, but drainage during healing is normal.
Pain and discharge should improve, and the openings should close. Follow-up matters because symptoms can return.
Sometimes. A repeat treatment may be reasonable, but the fistula should be reassessed first.
FiLaC is designed to avoid cutting the sphincter, so the risk is low, but no anal procedure has zero risk and existing symptoms matter.